IOC Editorial & Medical Information TeamPrepared with more than 22 years of bariatric-centre experience and checked against the official sources listed below. See our review process.
Instructions from your own surgical or prescribing team take priority over this general guide. Contact local emergency care for severe or rapidly worsening symptoms.
Key takeaways
- Follow the schedule given by your own surgical team; dates and textures are not identical for everyone.
- Hydration comes first, while protein and lifelong micronutrient monitoring support recovery.
- Persistent vomiting, inability to drink, fever, chest pain or worsening abdominal pain need prompt clinical advice.
Why the diet progresses in stages
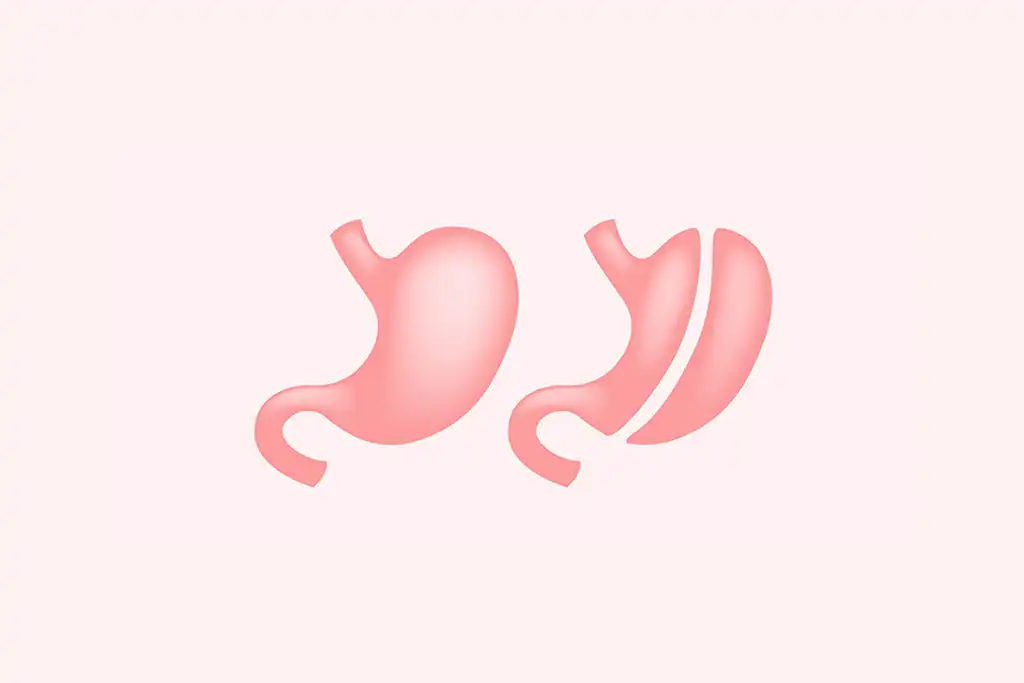
The staple line and surrounding tissues need time to heal. A staged plan moves from clear or thin fluids to smoother textures and then to soft and regular foods according to the team's protocol and the patient's tolerance.
Advancing faster is not a shortcut. It can increase pain, vomiting, dehydration and difficulty meeting nutrition goals.
Fluids and early recovery
Small, frequent sips are usually easier than large drinks. The team may ask you to separate drinking from meals later in the pathway. Sugary, fizzy and alcoholic drinks can cause symptoms or undermine weight-management goals.
- Keep the prescribed fluid target visible
- Use the team's sip schedule during the first days
- Watch urine colour and frequency as practical hydration clues
- Ask before using caffeine, supplements or electrolyte products
Protein, portions and eating behaviour
Protein supports healing and helps preserve lean tissue during rapid weight loss. The amount and source should be personalised by the bariatric dietitian, especially with kidney disease, food intolerance or a vegetarian diet.
Eat slowly, take small bites and stop at the first sign of pressure or fullness. Portion size is less important than tolerance, nutrition quality and consistent follow-up in the early stages.
Vitamins and blood monitoring
Reduced intake can lead to deficiencies even after a restrictive operation. Take only the bariatric supplements and doses recommended by your team, and complete scheduled blood tests. Iron, vitamin B12, folate, vitamin D, calcium and other markers may be monitored according to risk and local protocol.
Symptoms that should not wait
Contact the treating team promptly if you cannot keep fluids down, vomiting continues, swallowing becomes progressively difficult, or you develop fever, rapid heartbeat, shortness of breath, chest pain, black stools or increasing abdominal pain. Use local emergency services for severe or rapidly worsening symptoms.
See our gastric sleeve pathway
Understand the operation, hospital stay and one-year dietitian follow-up.
Open treatment pageFrequently asked questions
When can I eat normal food after gastric sleeve?
The date varies by protocol and recovery. Progress only when your own team confirms that the next texture is appropriate.
How much protein do I need?
Your bariatric dietitian should set the target from your body size, health, intake and recovery rather than a generic internet number.
Are vitamins lifelong after sleeve surgery?
Long-term supplementation and blood monitoring are commonly recommended. Your exact products and doses should follow your clinical team and test results.
What if I cannot drink enough?
Contact your treating team promptly because dehydration can worsen quickly after surgery; urgent symptoms require local emergency care.
Sources
This article was checked against the following official clinical and regulatory sources at its latest update.
NHS — Weight-loss surgeryNICE — Follow-up after bariatric surgery